NAD+ is the most-confused molecule in the longevity research catalog. It’s sold under three names (NAD+, NMN, NR), at three price points, with three completely different evidence bases. Where to buy NAD+ for research in 2026 requires resolving one question first: is the target molecule the cofactor itself, or a precursor (NMN or NR)? This guide covers the IV clinic markup, the oral precursor data, and the mass-spec check that confirms which molecule actually shipped.
Get new research first
Research updatesOne short email when new peptide research drops or a new lab-verified batch lands — written from primary sources, no filler.
You’re on the list — check your inbox for a confirmation.
Could not save your email. Try again in a moment.
Sourcing summary: research-grade NAD+ is available as lyophilized powder from research-supply vendors. A cofactor-grade CoA should confirm HPLC purity ≥99% and mass-spec at [M+H]+ 664.4. On November 17, 2026, US research suppliers listed it at $0.07–$0.47 per mg. The published human-trial evidence in the NAD+ literature is concentrated on oral NMN and NR precursors, not IV NAD+.
Three sourcing channels, and what each one offers
NAD+ has more channels than most peptides because it’s a small molecule, not a drug. Three options for actually getting it:
- IV NAD+ at a clinic: $500–$1,500 per session. Doctor on staff. 2–4 hour slow drip. The clinic uses a compounding pharmacy for material. No FDA approval for the marketed indications. Flush reactions (chest tightness, facial flushing, anxiety) are routine.
- Oral NMN or NR supplements: $60–$80 per month. No prescription. The molecule with most of the human RCT data. FDA rejected NMN as a dietary supplement in 2022, but enforcement has been patchy.
- Research-supply NAD+: $0.07–$0.47 per mg on November 17, 2026. Lyophilized powder under Research Use Only labeling. No prescription.
Gaps by channel. IV: zero RCTs for the marketed indications (addiction, senescence, cognition). Oral NMN/NR: studies have reported modest effects on biomarkers; long-term clinical outcomes data remain limited. Research-supply: no FDA-regulated batch testing, no physician oversight, and not intended for human use.
Identity and mechanism of NAD+
NAD+ is a cellular cofactor essential for metabolism. It carries electrons in cellular respiration. It feeds sirtuin enzymes (SIRT1 through SIRT7) and PARP enzymes (the ones that repair DNA). It also gets degraded by CD38, which rises with age (Covarrubias et al., 2021).
Here’s the wrinkle. NAD+ levels drop with age, which has fueled massive interest in “NAD+ boosting.” But the published human RCT evidence isn’t on direct NAD+. It’s on the oral precursors (NMN and NR).
The 2023 GeroScience dose-response trial randomized 80 middle-aged adults to placebo, 300, 600, or 900 mg NMN for 60 days. Blood NAD+ rose significantly in all NMN groups (Yi et al., 2023). That’s the molecule with the trial data. Not the IV NAD+ marketed by clinics.
“
Chronic nicotinamide mononucleotide supplementation elevates blood NAD levels and alters muscle function in healthy older men.
— Igarashi et al., NPJ Aging, 2022 (an NMN trial, not a NAD+ trial)
The four checks that matter for NAD+
The standard eight vendor criteria apply. Four are sharper here.
1. NAD+ vs NMN vs NR: molecular identity verification
This is the single most important step. The three molecules are not interchangeable:
- NAD+: MW 663.43, CAS 53-84-9. The cofactor itself.
- NMN (nicotinamide mononucleotide): MW 334.22, CAS 1094-61-7. The direct precursor. Most of the human trial data lives here.
- NR (nicotinamide riboside): MW 255.23, CAS 1341-23-7. Sold as NIAGEN by ChromaDex. Multiple human trials.
Vendors sometimes brand NMN or NR products as “NAD+ supplement” in the marketing copy while the ingredient line says NMN. Mass-spec catches it: NAD+ at [M+H]+ 664.4, NMN at 335.2, NR at 256.2. Hundreds of daltons apart. The test is unambiguous.
2. Form: lyophilized, light-protected, frozen
NAD+ is unstable in solution. The chemical bonds hydrolyze. Light degrades it. Oxygen oxidizes it. The stable shipping form is lyophilized powder, light-protected, kept at −20°C.
Pre-reconstituted NAD+ at room temperature ships with an unknown concentration at point of use. Nasal sprays and sublingual lozenges add a worse problem: NAD+ is a big polar molecule, and neither route has been validated in any published study.
3. Purity threshold: ≥99% HPLC, not ≥98%
Cofactor-grade standards are tighter than peptide standards. Where ≥98% is the peptide benchmark, ≥99% HPLC is the cofactor benchmark. Below 95%, the sample likely contains degradation byproducts (nicotinamide, ADP-ribose, ADP) that will confound experiments.
4. The IV-clinic markup, decoded
On November 17, 2026, US research suppliers listed 500 mg vials of NAD+ at $35.00–$100.00. The $1,000 IV-clinic price is real, but the material cost is a small slice. The rest is IV equipment, nursing labor and clinic overhead. See NAD+ IV vs oral precursors for the full math.
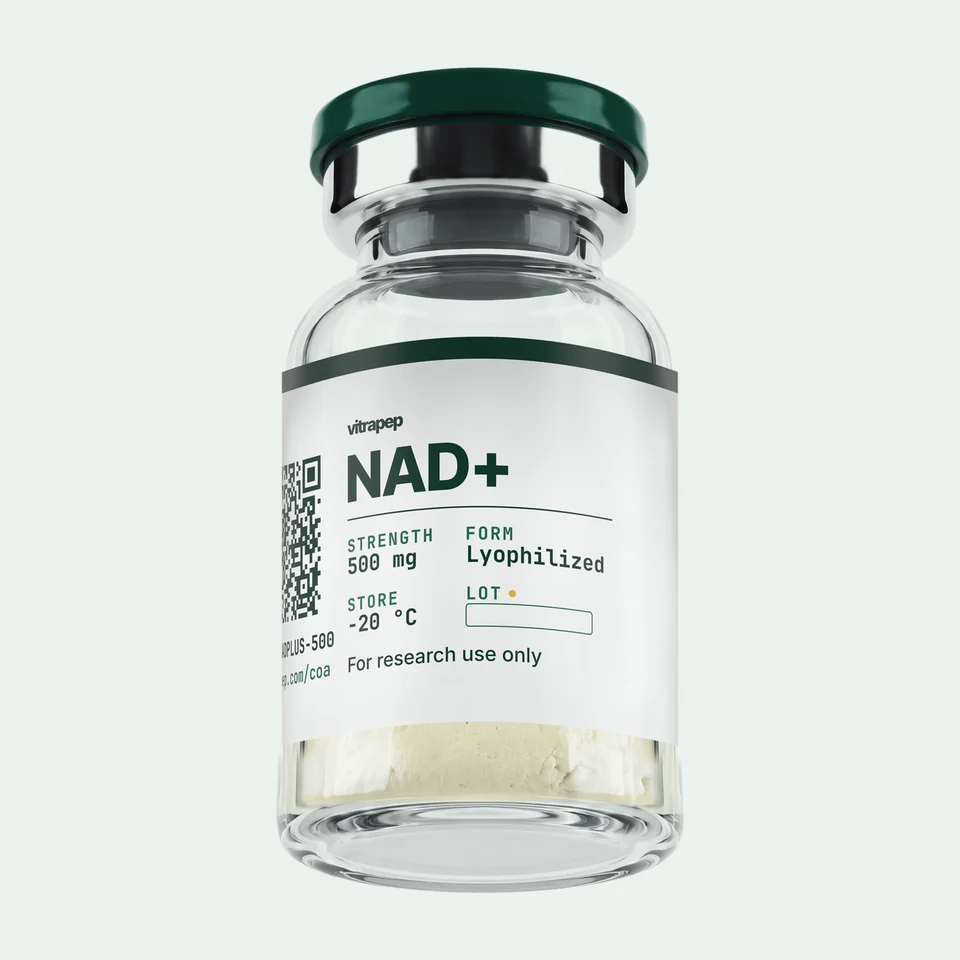
NAD+
The dinucleotide cofactor itself — not the cheaper NMN or NR precursor that vendors sometimes label as “NAD.” The same reference compound discussed across the 2021 Nature Reviews Mol Cell Biol NAD+ metabolism overview and the oral-precursor RCT literature anchoring our IV-vs-oral analysis. CAS 53-84-9, mass-spec confirmed at [M+H]+ 664.4, ≥99% HPLC purity, third-party CoA on every lot.
2026 pricing benchmarks
NAD+ pricing varies more than peptide pricing because of the cofactor-vs-research-grade split. We checked US research supplier product pages on November 17, 2026. Listed single-vial prices, before shipping and codes:
- 100 mg vial: $29.99–$47.00 ($0.30–$0.47 per mg).
- 500 mg vial: $35.00–$100.00 ($0.07–$0.20 per mg). Most common size. Best per-mg value for lab use.
- 1 g vial: $105.99 at the one supplier that showed a 1 g price ($0.11 per mg). Common for IV-clinic procurement.
- IV NAD+ clinic session: $500–$1,500 per session. Most of that is clinic markup, not material.
The full table, with each supplier and source, is on our peptide price list.
Below $30 per 500 mg vial, the pricing likely reflects partial degradation, underdosing, or rebranded NMN at NAD+ pricing. Far above the listed range, the premium typically represents retail markup rather than synthesis cost.
The legal picture
NAD+ regulatory status splits three ways:
- Research-use NAD+: Legal under 21 CFR § 809.10(b)(9) Research Use Only labeling. Not for human use.
- Oral NAD+ supplements: Not FDA-approved. Oral NAD+ also has poor bioavailability. The 2022 FDA rejection of NMN as a dietary supplement (on grounds it was being studied as a drug) was the more important decision in this lane.
- IV NAD+ at clinics: Sold via compounding pharmacies with no FDA approval for any specific indication. Operates under a different regulatory framework from research-compound sales.
WADA has not explicitly listed NAD+ or its precursors as of 2026.
Red flags specific to NAD+
- Vial labeled “NAD” without specifying NAD+, NMN, or NR. Three molecules. Hundreds of daltons apart. An order of magnitude apart in price.
- Nasal sprays or sublingual lozenges with stability claims. Neither route has been validated for NAD+ in any published controlled study.
- Pre-reconstituted solution at room temperature. NAD+ is unstable in solution; actual concentration at point of use is unknown without re-testing.
- Purity below ≥99% HPLC. Below 95%, the sample is likely to contain degradation byproducts.
- Pricing below $30 per 500 mg vial. Usually means degradation, underdosing, or rebranded NMN.
- Mass-spec not matching 664.4 [M+H]+. 335.2 means it’s NMN. 256.2 means it’s NR. No mass-spec at all means unverified identity.
- Clinical claims on the product page. “Treats addiction.” “Reverses aging.” That’s FDA jurisdiction.
NAD+ vs NMN vs NR — pricing and human-trial evidence by molecule and route.
The headline RCT evidence for “NAD+ boosting” sits with the oral precursors, not with IV NAD+. The IV-clinic pricing premium reflects clinic labor and slow-infusion time, not a material cost difference. Buyers should match their choice of molecule and route to the evidence base they care about.
Sources: published human-trial counts from Yi et al. (GeroScience 2023), Morifuji et al. (GeroScience 2024), Igarashi et al. (NPJ Aging 2022), Katayoshi et al. (Sci Rep 2023), Freeberg et al. (Front Cardiovasc Med 2022); pricing from 2026 vendor catalog survey + IV-clinic published rates.
NAD+
500 mg of cofactor-grade NAD+ at ≥99% HPLC purity — the same molecule discussed across our IV vs oral precursors cost-effectiveness analysis. Lyophilized pale-yellow powder, CAS 53-84-9, mass-spec confirmed at [M+H]+ 664.4. COA with HPLC trace and mass-spec ships with every order.
Frequently asked questions
Is NAD+ legal to buy?
Yes, as a research reference compound. NAD+ is a natural coenzyme present in every living cell. It’s not a controlled substance. The regulatory complications sit elsewhere: oral NAD+ isn’t FDA-approved as a supplement, IV NAD+ ships through compounding pharmacies without FDA approval for marketed indications, and the FDA rejected NMN as a dietary-supplement ingredient in 2022.
How much should NAD+ cost?
On November 17, 2026, US research suppliers listed 500 mg vials of NAD+ at $35.00–$100.00, or $0.07–$0.47 per mg across sizes. IV clinics bill $500–$1,500 per session, but the material is a small fraction of that price. Below $30 per 500 mg vial means partial degradation, underdosing, or rebranded NMN. Our peptide price list has the full table.
NAD+ vs NMN vs NR, which is best?
Three different molecules. NAD+ is the cofactor itself. NMN is the direct precursor. NR converts to NMN first. The published human-trial evidence sits with oral NMN and NR, not direct oral NAD+ (which has poor bioavailability). Research designed to align with the published precursor literature typically uses the NMN or NR form rather than NAD+ directly.
Why is IV NAD+ so expensive?
The NAD+ material is a small fraction of the $500–$1,500 session price. The rest is IV equipment, nursing labor and clinic markup. Whether IV beats oral NMN at a fraction of the cost is contested. See IV vs oral analysis.
Can I buy NAD+ without a prescription?
Yes, for research-grade powder under Research Use Only labeling. Clinical IV NAD+ at a clinic requires physician oversight and a compounding pharmacy. Two completely separate markets.
What should an NAD+ Certificate of Analysis show?
HPLC purity ≥99% with chromatogram. Mass-spec at [M+H]+ 664.4. CAS 53-84-9 on the identity line. Karl Fischer water content. Residual solvents per ICH Q3C (a pharmaceutical industry standard). Bacterial endotoxin testing if parenteral research is intended. An ISO 17025-accredited lab on the report. A CoA that doesn’t separately confirm NAD+ (rather than NMN or NR) is a critical gap.
What to know now
- CAS 53-84-9, MW 663.43, [M+H]+ 664.4. The identity values a cofactor-grade CoA should confirm.
- NAD+ is not a peptide. It’s a cofactor that lives in longevity catalogs because of co-marketing.
- NAD+ vs NMN vs NR is question one. Mass-spec disambiguates (664.4 vs 335.2 vs 256.2).
- $0.07–$0.47 per mg on November 17, 2026. The IV-clinic $1,000+ price is mostly labor, not material.
- Cofactor-grade purity is ≥99% HPLC. Tighter than the peptide ≥98% benchmark.
- Lyophilized powder, light-protected, −20°C. Pre-reconstituted, nasal, sublingual lack stability and pharmacokinetics data.
- The published human trials are on oral NMN/NR, not IV NAD+. Research matching that evidence base typically works with the precursor form.
What we’re watching
Three NAD+ developments matter most for 2026–2027. First: whether any randomized, blinded, sham-controlled IV NAD+ trial publishes for the marketed indications (addiction recovery, senescence, cognition). That absence is why the IV market stays contested. Second: the resolution of the FDA NMN status. The 2022 rejection blocked the dietary-supplement path, but the underlying question could reopen if pharmaceutical NMN trials reach Phase III. Third: the trial pipeline on oral NMN combined with senolytic drugs (compounds that clear damaged cells) or other longevity interventions. Single-agent NMN shows modest effects. Combinations may show larger signals.