Every blend vial is two purchases in one, and each half can fail independently. Where to buy CJC-1295 / ipamorelin blend in 2026 comes down to a question almost no product page answers directly: which CJC-1295 is actually in there? The name covers two chemically different molecules, and the mass-spec line on the Certificate of Analysis is the only place the truth shows up.
Get new research first
Research updatesOne short email when new peptide research drops or a new lab-verified batch lands — written from primary sources, no filler.
You’re on the list — check your inbox for a confirmation.
Could not save your email. Try again in a moment.
- CoA. Certificate of Analysis. A one-page lab report showing the specific lot’s purity, identity, and water content. For a blend it must cover each component separately.
- ISO/IEC 17025. The international quality standard for testing labs. A 17025-accredited lab has been audited by a third party for technical competence.
- DAC. Drug Affinity Complex. A maleimidopropionic acid linker attached to CJC-1295 that binds serum albumin and extends elimination half-life from minutes to days.
- Modified GRF 1-29. The other name for CJC-1295 without DAC. A 29-residue GHRH analog with a half-life measured in tens of minutes.
- 503A pharmacy. A U.S. compounding pharmacy licensed to make custom prescription medications for individual patients, operating under section 503A of the Federal Food, Drug, and Cosmetic Act.
- Co-lyophilized. Both peptides freeze-dried together into a single cake in one vial, rather than filled separately and combined later.
Quick answer. On November 17, 2026, US research suppliers listed no-DAC 10 mg blend vials at $45.00–$90.00. It should arrive as a co-lyophilized powder. The CoA should name the CJC-1295 variant explicitly, report two mass-spec identity lines (~3367.9 and ~711.9 g/mol), report purity per component rather than combined, and include a quantitative assay establishing the ratio. If the vendor cannot tell you whether the vial contains DAC or no-DAC material, the vial has no verified identity.
What you’re actually buying
A blend vial contains two unrelated molecules that happen to converge on the same cell. CJC-1295 is a 29-amino-acid synthetic analog of growth hormone-releasing hormone (GHRH 1-29), carrying substitutions that resist enzymatic degradation. Ipamorelin is a 5-amino-acid peptide (Aib-His-D-2-Nal-D-Phe-Lys-NH2) developed at Novo Nordisk in the late 1990s as a selective growth hormone secretagogue.
They are not variations on a theme. CJC-1295 binds the GHRH receptor on pituitary somatotrophs; it does not bind the ghrelin receptor at all. Ipamorelin binds the growth hormone secretagogue receptor 1a (GHS-R1a) — the receptor endogenous ghrelin uses — and does not touch the GHRH receptor (Memdouh et al., 2021; Lu et al., 2024).
That receptor separation is the entire reason the pairing exists. The two receptors sit on the same pituitary cell and route through different intracellular cascades, so activating both simultaneously produces a larger growth hormone pulse than the arithmetic sum of the two alone. A 2026 review in the Journal of the AAOS Global Research & Reviews groups CJC-1295 and ipamorelin together with sermorelin, tesamorelin, and AOD-9604 as growth hormone secretagogues acting through the GH/IGF-1 axis (Rahman et al., 2026). The pairing is mechanistically coherent. What it is not is clinically validated — a distinction covered in detail in our stack research review.
Legitimate blend material is a white lyophilized cake in a sealed glass vial, labeled with both component masses, the batch identifier, and a lot-matched CoA. The vial should state the CJC-1295 variant in words, not leave it to inference.
The DAC problem: two molecules, one product name
This is the single largest sourcing hazard specific to this blend, and it is a labeling problem rather than a chemistry problem.
“CJC-1295” is sold in two forms. The no-DAC form — also marketed as Modified GRF 1-29 — is the 29-residue GHRH analog with CAS 863288-34-0 and a molecular weight of 3367.9 g/mol (formula C152H252N44O42). The DAC form carries an additional lysine bearing a maleimidopropionic acid linker, which covalently attaches the peptide to circulating serum albumin and extends elimination half-life from minutes to days (Memdouh et al., 2021). That extra moiety carries its own CAS registration and adds roughly 280 daltons to the molecular weight.
Two molecules. One product name. Vendors routinely fail to specify which one is in the vial, and some list both variants under a single SKU with no analytical distinction on the paperwork.
For a blend, the ambiguity compounds. Blends are built on the no-DAC form because its half-life — on the order of tens of minutes — overlaps the window during which ipamorelin is active. The DAC variant’s multi-day half-life produces a temporal mismatch with a short-acting ghrelin mimetic, which is why it is a poor stacking partner in study designs examining pulsatile dynamics. A vial silently containing DAC material is not the compound the co-formulation rationale describes.
The good news: this ambiguity is trivially resolved by mass spectrometry. The two forms differ by hundreds of daltons, well outside any instrument’s tolerance. A CoA that reports an observed mass consistent with 3367.9 g/mol is reporting no-DAC material, full stop. Peptides this size typically appear in the spectrum as multi-charge ions, so expect the report to show [M+2H]2+ near 1684.9 or [M+3H]3+ near 1123.6 rather than a single [M+H]+ peak.
The one-line test. Ask a vendor: “Does the CJC-1295 in this blend carry the DAC modification, and what mass does your CoA report for it?” A supplier with real analytical documentation answers in one sentence with a number. A supplier that answers with marketing copy about synergy does not have the paperwork. There is no scenario in which a vendor holding a genuine third-party CoA cannot answer that question immediately.
The three places people buy it
The blend reaches buyers through three channels, and their relative importance has shifted materially since 2023.
1. Research-supply vendors (now effectively the only channel)
This is where nearly all U.S. buyers obtain the blend. The vendor sells a co-lyophilized vial labeled “for laboratory research use only.” That sale is legal under U.S. law; sale for human consumption is not, and the vendor is not a pharmacy.
Documentation to verify: a third-party CoA from an ISO 17025-accredited testing lab named on the report, separate identity and purity lines for each peptide, endotoxin testing by LAL, and residual-solvent or counterion content. The eight general criteria for any peptide vendor apply here in full, plus the blend-specific checks below.
2. 503A compounding pharmacies (a channel that closed)
This is the part of the story most product pages omit. Through the late 2010s and into the early 2020s, CJC-1295 with ipamorelin was one of the most frequently compounded peptide combinations in U.S. longevity-medicine clinical practice. It was a genuine prescription-adjacent product, dispensed by licensed 503A pharmacies against individual prescriptions.
That ended. FDA’s review of nominated bulk drug substances placed both CJC-1295 and ipamorelin in category 2, substances that may present significant safety risks. Both 503A nominations were later withdrawn; ipamorelin acetate stays in category 2 under the 503B policy. Across 2023–2025 the compounding channel for this pairing effectively closed. A 2026 Sports Medicine review classifies both molecules among unapproved peptide therapies where human safety data are scarce (Mendias & Awan, 2026).
Two consequences follow for buyers. First, any clinic or pharmacy still advertising compounded CJC/ipamorelin is operating outside the substance-eligibility framework, and its material carries no regulatory assurance above research-supply material. Second, a large volume of demand that previously ran through pharmacies migrated to research-supply vendors between 2023 and 2025 — which is precisely why the number of blend SKUs on the market expanded, and why documentation quality across those SKUs varies so widely.
3. Unverified gray-channel sellers
Social-marketplace listings, forum sellers, and drop-shipped storefronts with no named testing lab. A 2026 critical review in the Journal of Sports Medicine and Physical Fitness identifies the largely unregulated supply chain as the mechanism that turns a mechanistically-plausible compound into a documented hazard, citing mislabeled and contaminated products directly (Coutinho et al., 2026). For a two-component vial, the exposure doubles: either peptide can be underweight, substituted, or absent, and no visual inspection of a single white cake will reveal it.
The largely unregulated supply chain for performance peptides exacerbates the underlying dangers, with mislabeled and contaminated products documented as a real hazard alongside cardiovascular strain, insulin resistance, dyslipidemia, and psychiatric instability as emerging concerns.
— Paraphrasing Coutinho et al., Journal of Sports Medicine and Physical Fitness, 2026
The blend-specific checks
Four verification steps matter more for a two-component vial than they do for any single peptide.
1. Two CAS numbers, two masses, one report
A blend CoA carries two identity lines, not one. CJC-1295 no-DAC: CAS 863288-34-0, MW 3367.9 g/mol. Ipamorelin: CAS 170851-70-4, MW 711.9 g/mol, formula C38H49N9O5, with the observed [M+H]+ ion near 712.4.
If only one CAS number appears, the report is describing one peptide, and you do not know what the second component is — or whether there is one. A report that lists both CAS numbers but only one mass-spec result has the same problem in a subtler form.
2. Purity per component, never combined
HPLC purity is an area-percent figure: the target peak as a fraction of total peak area. On a two-peptide chromatogram that calculation is ambiguous unless the lab states which peak it applies to. A blend CoA reading “Purity: ≥99%” with no component breakdown is either sloppy reporting or a single-peptide report reused for a blend SKU.
What a correct report looks like: two purity figures, one per component, each with its own chromatogram or at minimum its own retention-time annotation. Anything less leaves open the possibility that one clean peptide is carrying the number for both.
3. Ratio verification requires quantitative analysis
This is the check most buyers skip, and it is the one that actually establishes you received what you paid for.
Purity tells you each peak is clean. It says nothing about how much of each peptide is in the vial. A vial containing 8 mg of ipamorelin and 2 mg of CJC-1295 can produce two immaculate ≥99% purity figures and still be nothing like a 5/5 blend. Establishing the ratio requires a quantitative method — quantitative HPLC against a characterized reference standard, or LC-MS with isotope-labeled internal standards — reported as mass per vial, not as a percentage.
One further subtlety worth knowing before you read a ratio claim. A “1:1” blend is a mass ratio, not a molar one. Because CJC-1295 is roughly 4.7× heavier than ipamorelin (3367.9 versus 711.9 g/mol), an equal-mass 5 mg + 5 mg vial contains roughly 1.5 µmol of CJC-1295 against 7.0 µmol of ipamorelin. Vendors who describe the blend as “equimolar” are describing a different product than the one they are selling.
4. Blend stability and the shorter in-use window
Lyophilized, both peptides are stable: the co-lyophilized cake holds at −20 °C for roughly 24 months and at 2–8 °C for about 6 months, and it survives room-temperature transit for the short durations shipping requires. That is the whole reason the material is sold freeze-dried.
Reconstituted, the picture changes, and it changes because of the CJC-1295 component. The no-DAC molecule’s solution stability is the limiting factor for the pair, which is why blend storage guidance sits around 14 days refrigerated rather than the longer windows sometimes quoted for ipamorelin alone. A vendor quoting a single generous in-use window without noting that the shorter-lived component governs it has not thought about the formulation. Pre-reconstituted blends sold without cold-chain shipping compound the problem and should be treated as a documentation gap rather than a convenience.
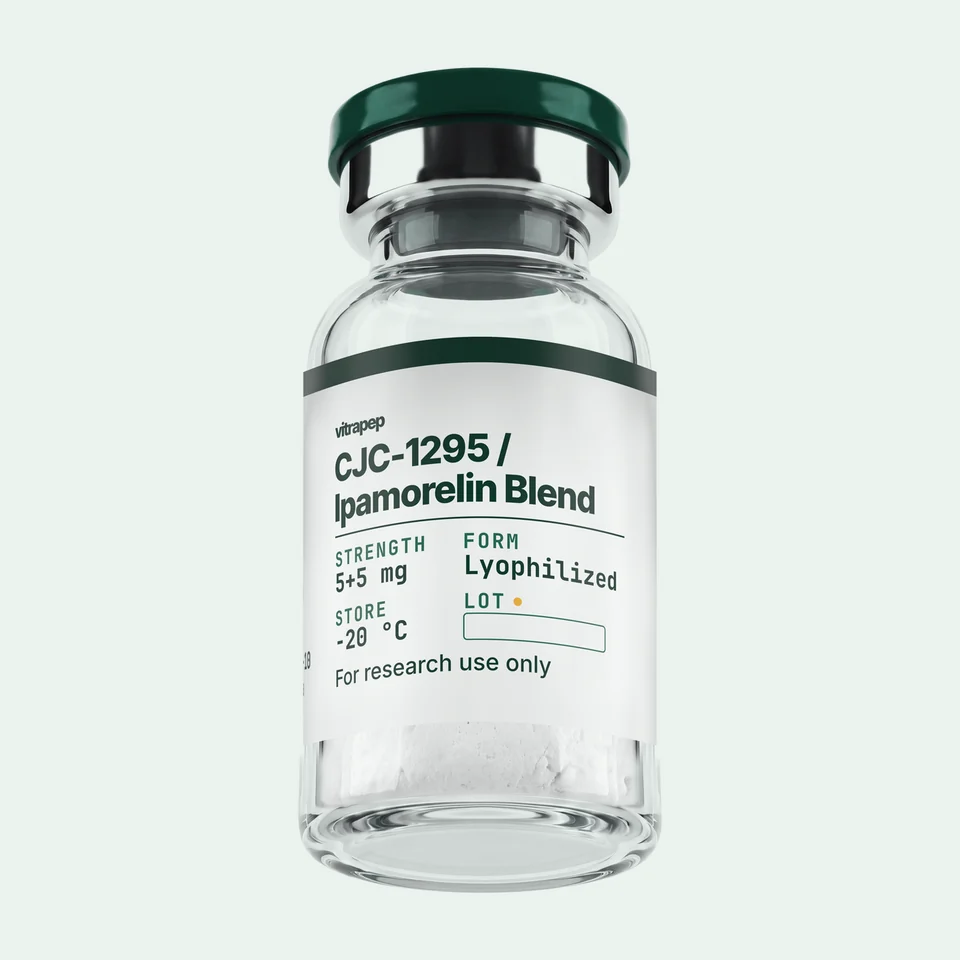
CJC-1295 / Ipamorelin Blend
The same two reference compounds cited across the anti-doping detection literature reviewed by Memdouh et al., 2021, the 2024 GHS-R1a cachexia model, and the 2026 JAAOS growth-hormone-secretagogue review. Explicitly no-DAC Modified GRF 1-29 at CAS 863288-34-0 (MS m/z 3367.9) co-lyophilized with ipamorelin at CAS 170851-70-4 (MS m/z 711.9), with per-component identity and purity on a third-party third-party CoA for every lot.
2026 pricing benchmarks
Blend pricing follows the combined peptide mass, adjusted down slightly for the fill economics of a single vial. Ipamorelin is only five residues, but two of them — Aib at position 1 and D-2-Nal at position 3 — are unnatural amino acids whose building blocks are expensive, so its per-milligram cost is far above what a pentapeptide would otherwise imply. CJC-1295 at 29 residues is a genuinely long synthesis. Neither component is cheap to make honestly.
- 10 mg blend vial (no-DAC): $45.00–$90.00 ($4.50–$9.00 per mg combined), on US research supplier product pages we checked on November 17, 2026. The standard retail size.
- Two-vial kit (5 mg CJC-1295 + 5 mg ipamorelin, filled separately): usually slightly above the single-vial blend because of the second fill.
- Multi-vial discounts: some suppliers discount larger orders.
The full table, with each supplier and source, is on our peptide price list.
Pricing far below the rest of the market deserves a direct question about which component was economized. The two most common ways to hit an impossible price are shorting one component — usually the expensive 29-residue one — or skipping the HPLC purification step that separates crude material from ≥98% material. A blend is a convenient place to hide the first, because a single white cake looks identical either way.
Above roughly $20/mg combined, you are paying retail markup rather than synthesis cost. The single-vial format should price at or slightly below the equivalent two-vial kit; a blend priced above the kit is charging a premium for the removal of your ability to verify each component independently.
Legal status: FDA, compounding, and WADA
Both components sit in the same regulatory position, which simplifies the analysis:
- United States (FDA): Neither component approved for any indication. Neither is a controlled substance. Legal to buy and sell as research reference material labeled for laboratory use only. Selling for human consumption is illegal; buying as research material is not.
- U.S. compounding: Both were placed in FDA’s category 2 (may present significant safety risks). The 503A nominations were withdrawn; ipamorelin acetate remains in category 2 under the 503B policy. The compounding channel for this combination effectively closed across 2023–2025.
- European Union (EMA): Neither approved.
- WADA: Both prohibited under category S2 (peptide hormones, growth factors, related substances and mimetics). See the WADA Prohibited List for current categorizations.
- Major sports leagues: Both prohibited.
- Detection: Validated LC-MS/MS methods identify CJC-1295 in urine and blood at sub-ng/mL concentrations (Cristea et al., 2023; Thomas et al., 2024).
The clinical-development history is worth knowing because vendors sometimes imply otherwise. CJC-1295’s therapeutic program was halted years ago and never revived. Ipamorelin advanced to a Phase III trial for postoperative ileus, missed its primary endpoint, and was discontinued. Neither molecule reached approval on any indication, and no randomized controlled trial of the combination for any clinical endpoint has been published.
Despite ipamorelin’s frequent appearance in grey-market protocols, robust human clinical evidence for performance, body-composition, or musculoskeletal-recovery indications is essentially absent.
— Paraphrasing Mendias & Awan, Sports Medicine, 2026
Red flags specific to the blend
- “CJC-1295” with no DAC designation anywhere. Not on the vial, not on the CoA, not on the product page. Two different molecules share that name, and the omission means the identity is unverified. This is the number-one blend-specific red flag.
- A single combined purity figure. “≥99% pure” on a two-peptide vial with no per-component breakdown. Area-percent purity across two peaks is not an interpretable number.
- No quantitative assay. Purity without a mass-per-vial assay leaves the ratio entirely unverified. A blend with immaculate purity figures can still be badly out of specification on composition.
- One mass-spec line for a two-component product. Both 3367.9 and 711.9 g/mol should appear, each with its observed ion.
- “Equimolar” or “1:1 molar” marketing on a 5 mg + 5 mg vial. An equal-mass blend is roughly 1:4.7 molar. A vendor describing it as equimolar is either careless with chemistry or copying someone else’s text.
- A generous reconstituted shelf-life claim. The shorter-lived component governs the blend. In-use windows quoted from ipamorelin data alone overstate the pair.
- Clinical or body-composition claims on the product page. “Builds lean mass.” “Reverses aging.” “Improves recovery.” No randomized controlled trial supports any of these for the combination, and a supplier making them has crossed into FDA jurisdiction.
- Compounding-pharmacy framing in 2026. A seller invoking pharmacy legitimacy for this combination is describing a channel that closed. Treat it as a marketing signal, not a quality signal.
- Single-source documentation. Internal QC is not sufficient. Third-party ISO 17025 verification is the standard, and for a blend it must cover both components.
What the 2020–2026 literature on these two peptides actually consists of.
Counting the PubMed-indexed record for CJC-1295 and ipamorelin across the 2020–2026 window by study type. The dominant categories are anti-doping detection methodology and narrative review — not efficacy research. Every primary animal study in the window tested a single agent; the most-cited combination finding reaches the literature secondhand, reported inside a 2026 review. Buyers should calibrate their evidence expectations to that shape.
Source: counts compiled from the 2020–2026 PubMed-indexed record for both molecules, including the detection-methodology series (Memdouh et al., 2021; Pont et al., 2020; Coppieters et al., 2022), the review record (Mendias & Awan, 2026; Mavrych et al., 2026), and the combination finding reported in Mayfield et al., 2026.
CJC-1295 / Ipamorelin Blend
Modified GRF 1-29 (no DAC, CAS 863288-34-0, MW 3367.9 g/mol) co-lyophilized with ipamorelin (CAS 170851-70-4, MW 711.9 g/mol, Aib-His-D-2-Nal-D-Phe-Lys-NH2). Research-grade reference material; per-component identity by LC-MS and per-component HPLC purity on the COA for every lot, plus endotoxin by LAL.
CJC-1295 combined with ipamorelin showed significantly improved maximum tetanic tension in murine models of glucocorticoid-induced muscle loss — but these findings are limited to animal studies.
— Paraphrasing Mayfield et al., American Journal of Sports Medicine, 2026
Frequently asked questions
Is the blend legal to buy in the USA?
Yes, as research reference material labeled for laboratory use only. Neither component is FDA-approved as a drug and neither is a controlled substance. Selling the blend for human consumption is illegal. Buying it as research material is not. Both components are WADA-prohibited under S2.
Does “CJC-1295” on a blend label mean DAC or no DAC?
You cannot know from the name alone — that is the entire problem. Blends are conventionally built on the no-DAC form (Modified GRF 1-29, CAS 863288-34-0, MW 3367.9 g/mol) because its half-life overlaps ipamorelin’s window, but conventions are not guarantees. The DAC form carries a maleimidopropionic acid linker, a separate CAS registration, and a molecular weight roughly 280 Da higher. The mass-spec line on the CoA settles it definitively; nothing else does.
What should a blend CoA show that a single-peptide CoA doesn’t?
Three things. Two mass-spec identity lines rather than one. Two HPLC purity figures rather than a combined number. And a quantitative assay reporting mass per vial for each component, which is the only test that establishes the ratio. See how to read a Certificate of Analysis for the general framework; the per-component requirement is the blend-specific addition.
Is one vial better than a two-vial kit?
They trade off. A co-lyophilized vial is cheaper and simpler to store, but the cake cannot be separated after filling, so the buyer is entirely dependent on the vendor’s quantitative testing for the ratio. A two-vial kit costs a little more and is easier to characterize component-by-component. For research designs where component identity must be independently confirmable, the kit is the more defensible format.
Can I still get this from a compounding pharmacy?
Not legitimately. This combination was among the most commonly compounded peptide pairings at U.S. 503A pharmacies through the early 2020s, but FDA’s bulk-substance review placed both components in category 2, substances that may present significant safety risks, and the channel effectively closed across 2023–2025. Sellers still invoking pharmacy framing in 2026 are describing history, not current regulatory standing.
How does the blend compare to buying each peptide alone?
It depends on the experimental question. A single-agent vial gives a cleaner readout when the question is about one receptor pathway; the blend is the right setup only when the question is specifically about GHRH-receptor and ghrelin-receptor co-stimulation. Our CJC-1295 vs ipamorelin comparison covers the receptor and half-life differences in full, and the single-compound sourcing guides for CJC-1295 and ipamorelin cover their individual verification requirements.
Are there analytical interferences worth knowing about?
One documented oddity. A 2021 method paper reported that certain cannabinoids — cannabidiol and carboxy-THC — act as allosteric ligands at the GHS-R1a receptor that ipamorelin targets (Danila et al., 2021). That finding was developed as a detection approach rather than as a characterization of the peptide, but it is a relevant confounder for any receptor-binding assay run on ipamorelin-containing material in a matrix where cannabinoids may be present.
How much evidence supports the combination specifically?
Less than the marketing implies. The 2020–2026 literature on both molecules is dominated by anti-doping detection methodology (6 papers) and narrative reviews (6), with only 3 primary animal studies, all single-agent. The combination finding most often cited — improved peak muscle force in rodent glucocorticoid-induced wasting — reaches the literature through a 2026 review rather than a primary paper. Human randomized trials of the combination: zero.
What to know now
- Two CAS numbers, two masses. CJC-1295 no-DAC at 863288-34-0 / 3367.9 g/mol and ipamorelin at 170851-70-4 / 711.9 g/mol. Both belong on the CoA, each with its own observed ion.
- The DAC question is the blend’s defining check. Two different molecules share the CJC-1295 name and differ by roughly 280 Da. If the vendor won’t say which is in the vial, the identity is unverified.
- Purity is not composition. Two ≥99% figures do not establish a 5/5 ratio. Only a quantitative assay reporting mass per vial does.
- “1:1” is a mass ratio. Equal masses are roughly 1:4.7 molar, because CJC-1295 is about 4.7× heavier than ipamorelin.
- $45.00–$90.00 per 10 mg blend vial on November 17, 2026. Two genuinely expensive syntheses — a 29-residue peptide and a pentapeptide built on unnatural amino acids — set a real floor under honest pricing.
- The compounding channel closed. Both components appear on FDA’s list of compounding substances that may present significant safety risks; the pharmacy route for this pairing ended across 2023–2025.
- The co-formulation itself has no primary literature. Six detection-method papers, six reviews, three single-agent animal studies, zero human RCTs of the combination.
What we’re watching
Three developments would change this guide. First, whether any vendor in this category moves to publishing a routine quantitative composition assay — mass per vial for each component, not just area-percent purity — as standard blend documentation. That single change would resolve most of what is currently unverifiable about two-component vials, and the labs are perfectly capable of it. Second, whether the post-503A migration of demand into research supply produces any convergence on labeling standards for the DAC-versus-no-DAC distinction, or whether the ambiguity persists because it is commercially convenient. Third, whether any registered trial of the combination appears on ClinicalTrials.gov for any indication. The pharmacology has been coherent for two decades; what has never existed is a controlled human readout, and until one publishes, the blend’s evidence base remains mechanism plus rodent data plus a large volume of analytical chemistry built to detect it.